Acne Vulgaris
An authoritative clinical profile of Acne Vulgaris covering AAD 2024 evidence guidelines, Cutibacterium acnes follicular dynamics, acne fulminans emergency red flags, and isotretinoin safety boundaries.
Editorial review complete
Independent clinical validation is pending.
Quick Reference Facts
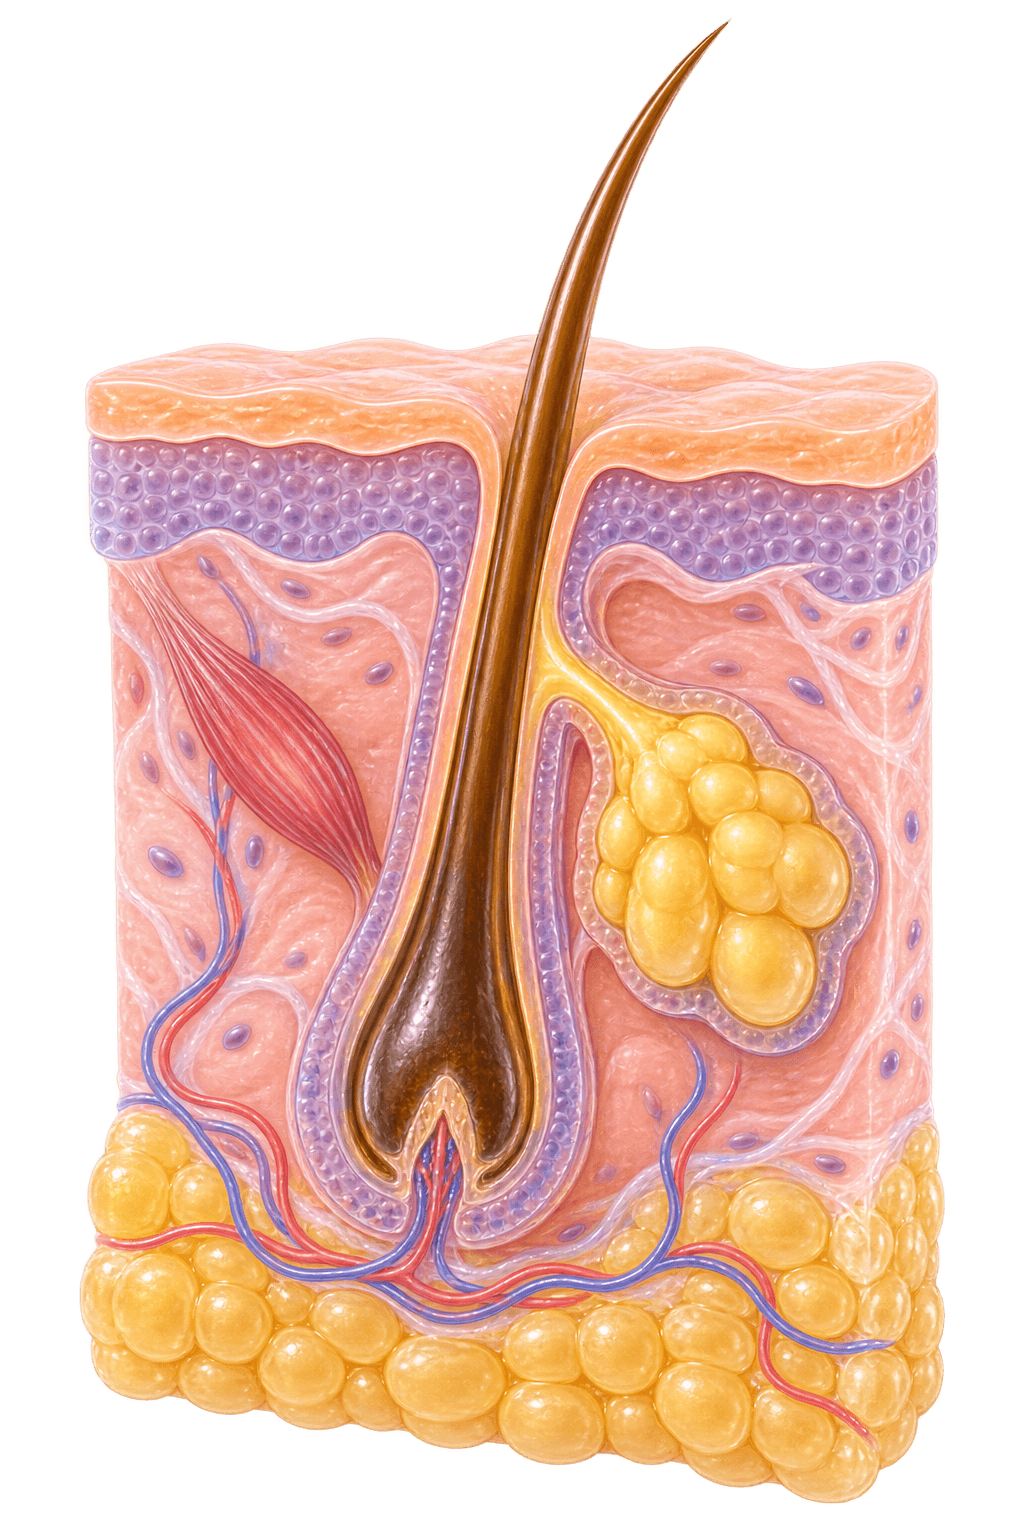
Visual guide
 Homeo Healthcare
 Homeo Healthcare
 Homeo Healthcare
In simple words
Acne Vulgaris is a chronic inflammatory dermatosis of the pilosebaceous unit characterized by follicular hyperkeratinization, seborrhea, Cutibacterium acnes proliferation, and inflammatory papules, pustules, nodules, or cysts [D0014-KEYNOTES, CIT-0046]. AAD 2024 classifies severity as mild, moderate, or severe.
A chronic multifactorial inflammatory disorder of hair follicles and sebaceous glands leading to comedones, inflammatory papulopustules, deep nodulocysts, and potential scarring.
Common causes
- Androgen-driven seborrhea and altered sebum lipid composition [D0014-KEYNOTES, CIT-0046]
- Abnormal follicular infundibular hyperkeratinization blocking sebum outflow
- Follicular colonization by Cutibacterium acnes triggering innate and adaptive cutaneous immunity
Risk Factors
- Adolescent and young adult hyperandrogenemia or PCOS
- Family history of severe nodulocystic acne and keloidal scarring
- Use of comedogenic cosmetics, topical corticosteroids, or systemic medications (lithium, anticonvulsants)
Common symptoms
- Non-inflammatory comedones (open blackheads, closed whiteheads) and inflammatory papules/pustules [D0014-KEYNOTES, CIT-0046]
- Painful deep erythematous nodulocysts located on face, chest, upper back, and shoulders
- Post-inflammatory hyperpigmentation (PIH), erythematous macules, and permanent atrophic/hypertrophic scarring
Lifestyle & diet support
Cleanse face twice daily with a mild non-comedogenic cleanser, avoid aggressive scrubbing or popping lesions, apply oil-free sunscreen, and consume a balanced low-glycemic diet.
Treatment Approaches
Conventional Management
Management includes topical benzoyl peroxide, topical retinoids (adapalene, tretinoin), topical/oral antibiotics (doxycycline), hormonal therapy (COCPs, spironolactone), and oral isotretinoin for severe recalcitrant nodulocystic acne [CIT-0046].
Homeopathic Approach
Homeopathic remedies (such as Hepar Sulphuris, Silicea, Sulphur, Pulsatilla, Berberis Aquifolium) act as supportive constitutional therapy to soothe cutaneous inflammation, reduce pustular suppurative tendency, and promote skin healing alongside dermatological evaluation.
Frequently Asked Questions
Clinical & academic detailShow detailHide detail
Diagnosis & tests
Investigation Protocol
Diagnosed clinically via skin examination assessing lesion type, distribution, and severity grading (Global Acne Grading System). Hormonal evaluation (testosterone, DHEAS) indicated if hyperandrogenism signs exist [CIT-0046].
Differential Diagnosis
Differentiate Acne Vulgaris from Rosacea, Folliculitis (Malassezia/bacterial), Perioral Dermatitis, Hidradenitis Suppurativa, and Drug-Induced Acneiform Eruptions.
Differential Diagnosis Matrix
Differentiate Acne Vulgaris from Rosacea, Folliculitis (Malassezia/bacterial), Perioral Dermatitis, Hidradenitis Suppurativa, and Drug-Induced Acneiform Eruptions.
Reference Citations & Evidence Sources
Clinical Guidelines & Consensus Statements
Primary Clinical Research & Trials
- CIT-0002Witt C. M., Lüdtke R.. "Individualized Homeopathic Treatment for Atopic Dermatitis: A Cohort Study." Complementary Medicine Research (2019).
Clinical Reviews & Textbooks
- CIT-0022Jethwani N.. "Internal Clinical Review Note: Standard Reference Values and Homeopathic Therapeutic Mappings for Lab Diagnostics." Homeo Healthcare Internal Review Series (2026).
No clinical connections registered for this topic.
Seeking Expert Consultation?
Book an online video session with Dr. Narayan Jethwani to get an individualized constitutional homeopathic protocol tailored to your case.
Medical Safety Disclaimer
All content on the Homeo Healthcare platform is strictly for educational purposes and is not personal medical advice, diagnosis, or treatment. Homeopathic remedy considerations are provided for clinician review or require individualized consultation with a qualified physician. Never delay seeking professional medical advice or emergency medical care due to content you have read on this website.